How do ventilators help patients breathe? The answer begins with a simple distinction: a ventilator supports breathing, but it does not cure the illness that made breathing difficult. Critical-care physician Dr. Martin J. Tobin has described mechanical ventilation as a means of supporting patients whose respiratory muscles cannot meet the body’s needs. In plain language, the machine helps move air; clinicians still need to diagnose and treat the cause.
A ventilator may deliver oxygen-rich air through a mask or a breathing tube, depending on the patient’s condition. With each supported breath, air travels into the lungs, where oxygen can pass into the blood and carbon dioxide can leave. The machine’s settings are adjusted to the individual. Clinicians watch the patient’s chest rise, check oxygen levels, and review blood tests. Small changes can matter.
That support can give tired muscles time to rest. It can also feel unfamiliar or uncomfortable, especially when a breathing tube is used. Ventilation is not a one-size-fits-all solution, and more assistance is not always better. Care teams continually reassess whether the support is helping and when it may be reduced. The details depend on the patient, the underlying condition, and the response to treatment. A ventilator assists. People provide the care.
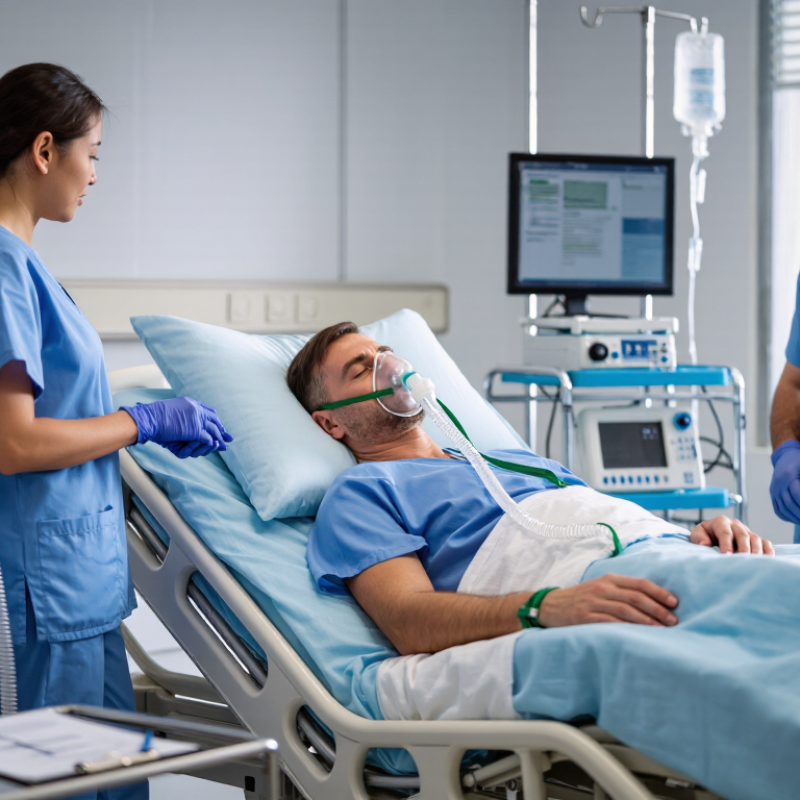
A ventilator supports breathing when illness, injury, or surgery makes it difficult to move enough air. It delivers air, often with added oxygen, through a mask or a tube placed in the airway. Pressure helps air reach the lungs, where oxygen passes into the blood and carbon dioxide is removed. The machine can provide breaths on a set schedule or assist when a patient begins breathing.
It is not simply a machine that “breathes for someone.” Clinicians adjust settings to match the person’s condition, breathing effort, and test results. They monitor oxygen levels, carbon dioxide, chest movement, and comfort. Small changes can matter. A mask may feel tight; a breathing tube can make speaking impossible. Ventilation also carries risks, including lung irritation or infection, so teams reassess the need for support regularly. The right settings are not always obvious at first, and care may need careful adjustment as the patient’s condition changes.
| Dimension | What the Ventilator Does | How This Supports the Patient | Important Context |
|---|---|---|---|
| Air movement | Moves air, or an air-and-oxygen mixture, into the lungs through a breathing circuit. | Helps deliver breaths when a person cannot breathe adequately on their own. | A ventilator supports breathing; it does not treat every cause of respiratory illness. |
| Oxygen delivery | Allows clinicians to set the oxygen concentration delivered with the breaths. | Can help raise the amount of oxygen available to pass from the lungs into the blood. | The required oxygen concentration depends on the patient’s condition and is monitored by the care team. |
| Carbon dioxide removal | Provides breaths that help move carbon dioxide out of the lungs. | Supports gas exchange when breathing is too weak, slow, or otherwise ineffective. | Breath size and rate are selected with the patient’s condition and test results in mind. |
| Breath support | May deliver breaths on a set schedule, assist breaths initiated by the patient, or combine these approaches. | Can provide more or less assistance depending on how much the patient can breathe independently. | The mode and settings are chosen by qualified clinicians and may change over time. |
| Connection to the patient | May deliver support through a mask or, for invasive ventilation, through a tube placed in the windpipe. | Provides a route for air to reach the lungs. | The appropriate method depends on the person’s needs, ability to protect their airway, and clinical situation. |
| Monitoring | Displays information such as delivered breaths, pressures, and alarms; clinicians also assess the patient and review tests. | Helps the care team evaluate how well respiratory support is working and identify changes that may need attention. | Ventilator readings are interpreted alongside the patient’s examination and other clinical information. |
| Adjustment of support | Settings can be adjusted to match changing respiratory needs. | Allows support to be tailored while the patient recovers or their condition changes. | Settings should be managed by trained healthcare professionals, not adjusted by patients or bystanders. |
| Potential risks | Mechanical ventilation can involve risks, including lung injury, infection, or irritation related to the breathing tube. | Care teams use monitoring and preventive measures to reduce risks where possible. | Risks vary with the patient, the reason for ventilation, and how long support is needed. |
| Reducing support | When appropriate, clinicians gradually assess whether ventilator assistance can be reduced or stopped. | Supports a safe transition back to independent breathing when the patient is ready. | The timing depends on the underlying illness and the patient’s ability to breathe and protect their airway. |
Note: Ventilator support is individualized. The device, settings, and duration of treatment are determined by the healthcare team based on the patient’s condition.
It moves measured air into the lungs through a mask or breathing tube. Oxygen enters the blood, while carbon dioxide leaves. It supports the lungs; it does not replace them.
A snug mask delivers air under pressure. In other situations, a tube passes through the mouth into the windpipe. The care team chooses support for the patient’s needs.
Settings shape breath size, timing, and pressure. Clinicians also choose a breathing mode. Small changes matter.
Volume-controlled breathing aims to deliver a selected amount of air per breath. Pressure-controlled breathing limits pressure, so the delivered air volume can vary.
The breathing rate sets a minimum number of breaths per minute. PEEP maintains some pressure after exhalation, helping keep tiny air sacs open. Too much pressure can cause harm.
They review oxygen readings, breathing rate, air volume, and pressure. They also watch chest movement, skin color, comfort, and effort. A finger sensor gives one clue, not the whole story.
A loose connection can trigger an alarm, as can a change in the patient’s condition. Alarms prompt assessment; they are not diagnoses. Do not silence alarms or change settings yourself.
Notice loose tubing, a shifted mask, or new distress, and alert the care team. Ask what an alarm or reading means. The explanation may feel incomplete. It is okay to ask again.
A ventilator supports breathing when a person cannot move enough air into and out of the lungs on their own. It delivers a carefully controlled flow of air, often with added oxygen, through a breathing tube or a fitted mask. The machine can help inflate the lungs and make it easier for the body to receive oxygen and remove carbon dioxide. In explaining how do ventilators help patients breathe, it is important to note that the device supports breathing rather than treating every underlying cause of respiratory illness.
Clinicians set and adjust factors such as breath size, pressure, rate, and oxygen level according to the patient’s needs. They monitor breathing, oxygen levels, and other signs of response, then make changes as needed to provide appropriate support. Ventilation may be used temporarily during serious illness, surgery, or recovery. When a patient can breathe adequately with less assistance, clinicians gradually reduce support and assess whether the ventilator can be discontinued safely.

 QMS Medical